By Robert Clifton September 30, 2026
There is no universal rule requiring one merchant ID for every physician, NPI, or medical-practice location. The right merchant account structure medical group leaders choose depends on legal entities, ownership, settlement accounts, payment locations, reconciliation requirements, patient-facing descriptors, PM/EHR architecture, acquired practices, refund controls, and the processor or acquirer’s underwriting requirements.
That distinction matters because healthcare organizations work with several identification systems at once. A TIN, NPI, practice location, merchant account, MID, processor profile, and settlement bank account may need to be mapped to one another, but they do not identify the same thing and should not be treated as interchangeable.
Merchant Account Structure Medical Group: Quick Comparison
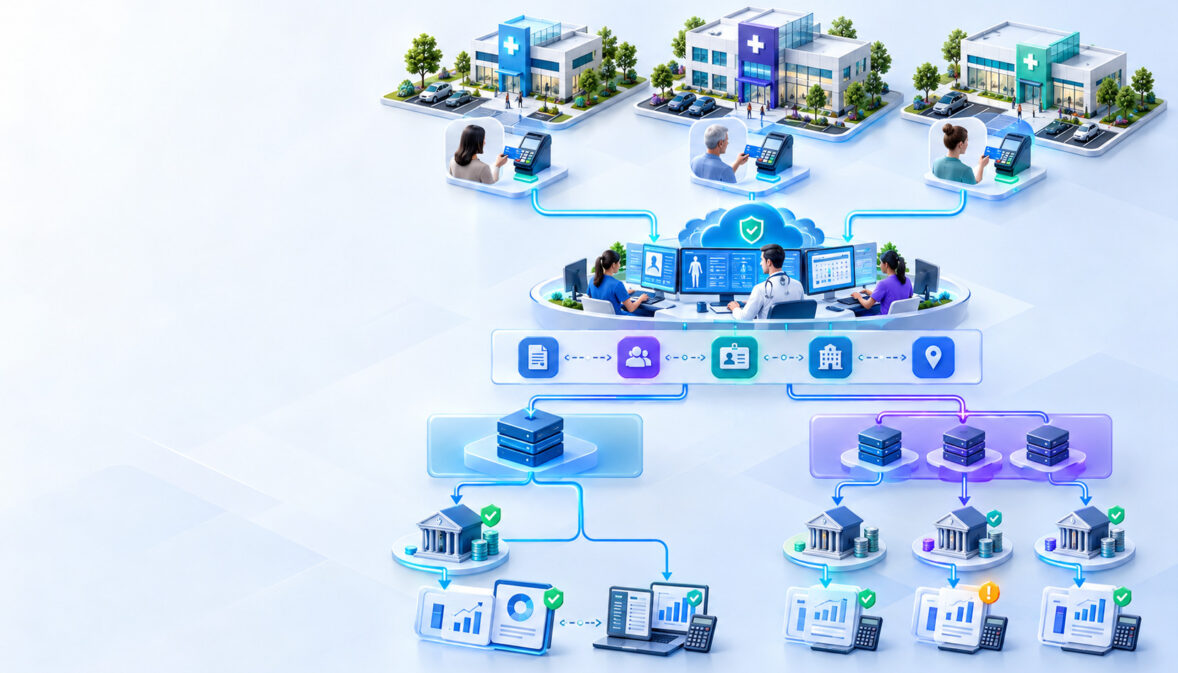
A merchant account structure medical group administrators can reliably operate does not necessarily mean choosing between one MID for everything and one MID for every clinic. Many groups use a consolidated structure, location-level MIDs, entity-level merchant arrangements, or a hybrid model.
| Structure | Usually Fits | Deposit Reporting | Reconciliation | Descriptor Control | Dispute Visibility | Operational Complexity |
| One MID across multiple locations | Same merchant/legal entity, centralized banking and billing, reliable location metadata | More consolidated | Efficient when PM/gateway tags every transaction correctly | Often more centralized; configuration depends on processor/acquirer | Less processor-native separation by site | Lower |
| Separate MID per location | Clinics need separate deposits or processor-native location reporting | Clearer by clinic | Easier to connect a site’s batches to its deposits | May allow greater location differentiation, subject to processor configuration | Easier to attribute activity to a clinic | Moderate to high |
| Separate merchant setup by legal entity | Different entities own receivables or settlement accounts | Naturally segregated | Cleaner entity-level accounting | Can align with each merchant of record | More direct entity-level attribution | Higher |
| Hybrid structure | Large groups, acquisitions, mixed banking structures, centralized and decentralized operations | Configurable | Strong if mappings and controls are maintained | Potentially flexible | Can preserve useful segmentation | Highest design burden |
No row is universally “best.” The correct structure is the one that lets the organization trace a patient payment from collection through the patient ledger, processor transaction, batch, refund or dispute activity, and final bank deposit without confusing the group’s healthcare identifiers with its payment-processing identifiers.
First, Separate Legal Entities, TINs, NPIs, Locations, Merchant Accounts, and MIDs
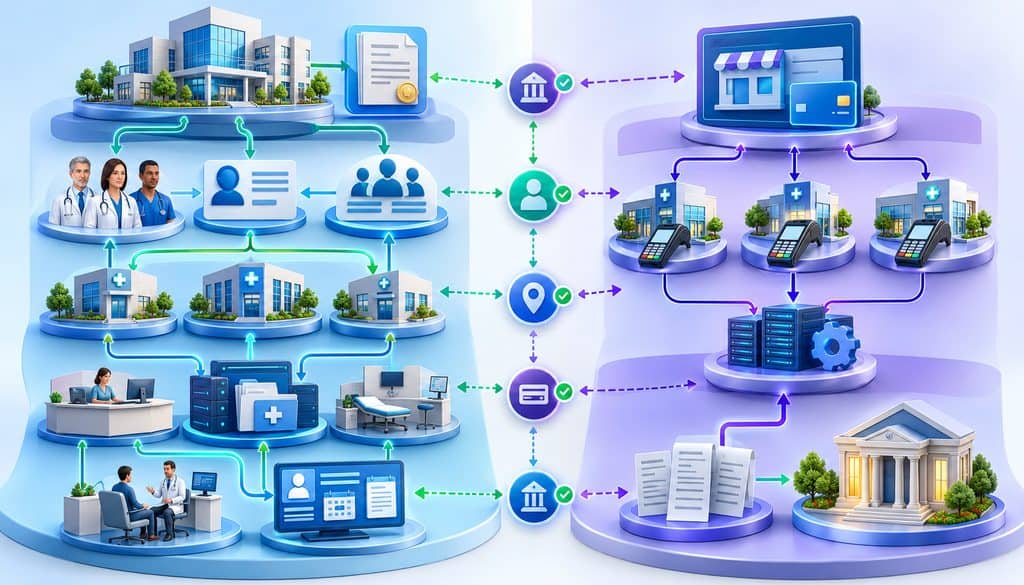
CMS’s current National Provider Identifier guidance defines the NPI as the standard unique identifier for healthcare providers, distinguishes Type 1 NPIs for individuals from Type 2 NPIs for organizations, and makes clear that obtaining an NPI does not itself enroll a provider in a health plan or guarantee payment.
That provides an important starting point for designing a merchant account structure medical group administrators will not confuse with payer enrollment.
| Identifier or Structure | What It Actually Represents |
| Legal entity | The corporation, LLC, partnership, professional entity, sole proprietorship, or other person conducting the business |
| EIN/TIN | Taxpayer identification used for the relevant person or organization |
| Type 1 NPI | NPI assigned to an individual healthcare provider |
| Type 2 NPI | NPI assigned to an organizational healthcare provider |
| Organizational subpart | A component of an organization that may have or require its own Type 2 NPI under applicable NPI rules |
| Practice location | Physical or enrolled place where healthcare is furnished or reported |
| Merchant account | Commercial arrangement allowing the merchant to accept card payments through an acquirer/processor |
| MID | Merchant identifier associated with a particular acquiring or processor configuration |
| Processor/merchant profile | Processor-side configuration governing channels, terminals, settlement, reporting, permissions, and related settings |
| Settlement account | Bank account to which card-processing proceeds are credited |
| PM/EHR department or location | Software dimension used to assign encounters, patient payments, providers, departments, or sites |
TIN and legal entity
A TIN identifies a taxpayer for tax and reporting purposes. The legal entity identifies the business or person entering agreements and owning the relevant operations.
Those facts can matter greatly to merchant underwriting. If two clinics are owned by genuinely different legal entities, receive funds into separately owned accounts, or have different merchant-of-record relationships, the processor or acquirer may require different merchant arrangements.
That is an acquiring and contractual question—not a rule that can be derived merely from the number of NPIs.
Type 1 and Type 2 NPIs
CMS’s current guidance states that a Type 1 NPI applies to an individual provider, such as a physician or nurse practitioner, while a Type 2 NPI applies to an organization such as a physician group or hospital. An individual healthcare provider is eligible for only one Type 1 NPI, while an organization can have multiple NPIs.
CMS has also historically recognized organizational “subparts.” A subpart is not automatically a different legal entity. Depending on the circumstances and the HIPAA standard transactions conducted by that part of the organization, an organizational subpart may have its own NPI.
None of those CMS rules establishes a one-NPI-equals-one-MID requirement.
Practice locations are another separate layer
CMS’s current NPPES downloadable-file documentation separately identifies a Practice Location Reference File containing non-primary practice locations associated with Type 1 and Type 2 NPIs.
That structure reinforces an important operational distinction: an NPI can be associated with location information, but an NPI and a practice location are not the same identifier.
That is useful evidence for a basic operational principle: an NPI, an organizational subpart, and a practice location are related concepts, but they are not interchangeable.
Merchant accounts and MIDs
The MID belongs to the acquiring/payment-processing architecture. CMS does not assign a merchant’s card-processing MID, and an NPI is not a substitute for a MID.
Likewise, a merchant account is not automatically the same thing as a bank account. One merchant setup may settle into a particular deposit account, but the processor relationship, merchant identifiers, terminal profiles, gateways, and settlement banking remain distinct pieces of the payment architecture.
Map the systems instead of collapsing them together
A useful mapping for a multi-location organization might look like:
Legal entity → TIN → organizational NPI/subpart → practice location → PM/EHR location → gateway profile → MID → settlement account
Provider attribution can be added alongside the encounter:
Patient account → encounter → rendering/billing provider → clinic/department → payment transaction → MID → batch → deposit
This is one of the most important design principles in the article: payer enrollment architecture and card-processing architecture are different systems.
A Medicare, Medicaid, or commercial-payer requirement should not be described as an acquiring-bank requirement merely because both systems use information about the provider. Likewise, an acquirer’s underwriting policy should not be called a CMS, NPI, or HIPAA requirement.
The site’s explanation of the difference between medical billing and merchant services provides useful operational context for keeping claim/payment workflows separate from card settlement.
One MID or Multiple MIDs: What Actually Changes?

Once legal ownership is properly mapped, the next question is what separate MIDs change operationally.
For most organizations, the answer involves settlement visibility, refund authority, statement descriptors, dispute attribution, device and gateway configuration, and the amount of administrative work required to maintain the system.
Deposit and settlement reporting
With one MID, processor reports may consolidate several locations into one merchant-level view. A group can still produce location-level reporting if its gateway, PM system, or integration reliably stores the location with every transaction.
With a MID per location medical practice structure, settlement reports can be easier to segment natively. A batch from Clinic A can be associated with Clinic A’s merchant profile instead of requiring accounting to divide a consolidated merchant report after settlement.
That distinction becomes especially valuable when clinics maintain separate operating accounts.
Statement descriptors
Patients often recognize the healthcare organization differently from the way the acquiring relationship is legally configured.
A multi-location group may want the cardholder statement to show the medical group, a clinic DBA, or some other recognizable descriptor. Whether that can vary by MID or location depends on the processor, acquirer, network-compliant configuration, and merchant setup.
Do not assume that adding another MID automatically produces a unique descriptor. Test the actual production configuration before relying on it.
Refund reporting
Location-level MIDs can make it easier to identify which location originally collected and refunded a payment. They can also make cross-location refunds harder when users at another site do not have access to the original merchant profile.
A consolidated model may simplify centralized refunds but make processor-native site attribution weaker.
The refund design should therefore be tested before the merchant account structure medical group adopts is finalized.
Chargebacks and dispute visibility
Separate MIDs can help accounting or revenue-cycle teams attribute disputes to the site that accepted the payment. That can make it easier to investigate location-specific issues such as unclear patient communications, refund delays, payment-plan confusion, or terminal workflows.
Separate MIDs should not be sold internally as guaranteed risk isolation.
The merchant’s processor or acquiring bank may evaluate risk at more than one level, including the merchant relationship, common ownership, legal entities, processing history, or other underwriting factors. No universal promise should be made that a problem involving one MID can never affect related merchant relationships.
Does Every Medical Practice Location Need Its Own MID?
No. A separately enrolled or physically separate clinic does not automatically require a separate merchant ID.
A MID per location medical practice design becomes more attractive when each clinic needs its own settlement account, processor-native reporting, local refund ownership, different hardware or payment channels, or reliably differentiated merchant configuration.
A consolidated structure may make more sense when:
- the clinics operate under the same merchant/legal entity;
- one treasury or billing department controls patient collections;
- funds settle into a common account;
- patients regularly move between clinics;
- refunds are centralized;
- the PM/EHR reliably records the location for each payment; and
- accounting can reconcile every clinic without relying solely on the MID.
Consider three clinics under one entity using the same bank account and the same PM system. If each card transaction contains a dependable location code and processor transaction ID, the group may already have enough information for clinic-level reporting without three independent merchant environments.
Now consider three clinics whose collections must settle into three separate bank accounts. In that case, location-specific merchant profiles or another processor-supported split-settlement architecture may substantially simplify medical practice settlement reporting.
The key is not the address alone. It is the combination of ownership, settlement, operational responsibility, processor capabilities, and reporting requirements.
Does Every Doctor or NPI Need a Separate Merchant Account?
No general CMS or acquiring rule says a medical group must create a merchant account for each physician simply because each physician has a Type 1 NPI.
In most group-practice environments, provider-level attribution belongs primarily in the PM/EHR or accounting system. That is where the organization already knows which physician rendered the service, which provider billed the encounter, which department owns the balance, and which patient account received the payment.
A merchant account structure medical group creates at the physician level should therefore be treated as an exception that needs a clear operational reason.
Ask:
- Does the money legally belong to the physician or to the group?
- Which entity is the merchant of record?
- Which bank account should receive settlement?
- Who issues patient refunds?
- Who responds to disputes?
- Does the patient recognize the statement descriptor?
- Does the PM/EHR already provide provider-level payment reporting?
- Is the physician operating as a separate business?
- Will the acquirer underwrite the proposed relationship as structured?
Creating one MID for every clinician merely to obtain provider-level reports can create unnecessary fragmentation. Patient credits, provider cross-coverage, centralized billing, staff permissions, refunds, terminal selection, and multi-provider payment reconciliation may all become harder.
How Payer, Audit, and Cost-Reporting Needs Affect the Structure
Healthcare collections contain several financial layers that do not exist in ordinary retail.
A medical group may need to distinguish:
- payer remittances;
- patient responsibility;
- copays;
- deductibles;
- coinsurance;
- self-pay balances;
- pre-service deposits;
- patient refunds;
- unapplied credits;
- card-processing fees;
- chargebacks; and
- card settlement deposits.
The same payment may also need attribution to a practice location, legal entity, department, rendering provider, billing provider, encounter, patient account, date of service, or financial class.
That does not mean every attribution dimension requires its own MID.
Reporting granularity does not necessarily require merchant-account fragmentation if the processor, gateway, and PM/EHR preserve reliable transaction, location, encounter, department, and provider metadata.
This is where multi-provider payment reconciliation should be designed independently from the number of merchant accounts.
For example, a consolidated $30,000 bank deposit could contain payments from several clinics. Accounting still needs to know which underlying transactions produced the deposit, but it does not need to pretend that each clinic received a separate bank transfer if the processor actually sent one consolidated settlement.
The patient ledger allocation and movement of processor cash are different accounting events.
What Happens When a Patient Pays at Location A but Is Seen or Refunded at Location B?
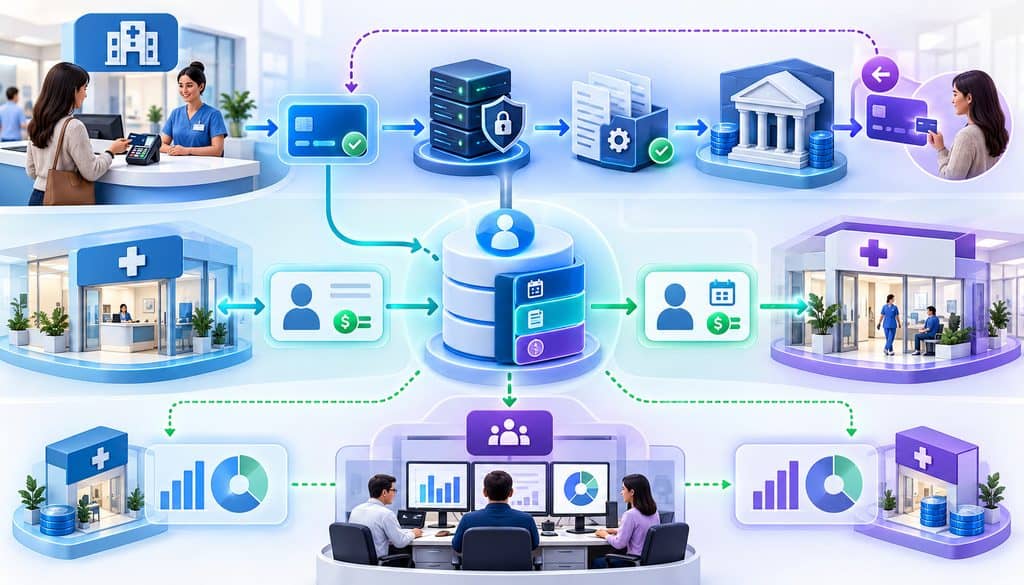
Keep the original payment transaction as the processor-side source of truth.
Suppose a patient pays an estimated amount at Clinic A. The appointment later occurs at Clinic B, and the PM system determines that the patient credit should be applied to the encounter at Clinic B.
If the same legal entity owns the patient receivable, staff may be able to reallocate the credit in the patient ledger without refunding the original card transaction and creating a new charge.
That workflow should separate three concepts.
1. Processor-side payment mechanics
Preserve:
- original transaction ID;
- original MID or merchant profile;
- authorization/reference information;
- original amount;
- batch;
- settlement date; and
- any eventual refund transaction.
2. Patient-ledger accounting
The PM system should show where the payment is ultimately applied: the correct patient balance, encounter, provider, department, or location.
3. Internal management allocation
Accounting may need to move revenue or collection attribution from Clinic A to Clinic B without moving cash at the processor.
That is a bookkeeping allocation, not necessarily a second payment transaction.
Do not create artificial refund-and-recharge loops
If an internal PM reallocation solves the problem, staff generally should not create a refund and new card charge solely to shift location attribution.
Doing so can create unnecessary patient confusion, duplicate authorization activity, additional settlement differences, and broken audit trails.
Which MID should issue the actual refund?
Start with the original transaction.
A processor may require or support refunding through the merchant environment associated with the original sale, but actual capabilities and controls differ by processor and implementation. The group should document who can access and refund transactions taken at each site rather than inventing a universal network rule.
If Clinic B cannot access Clinic A’s original merchant profile, the centralized billing team or another authorized user may need to process the refund from the original payment workflow.
When payments move through several front desks, portals, and billing teams, automating routine medical-practice payment workflows can reduce duplicate data entry and make it easier to preserve consistent transaction records across locations.
One MID vs Many: HIPAA and BAA Considerations
MID count does not determine HIPAA compliance.
A group with one MID can have serious HIPAA problems if PHI is exposed improperly. A group with 20 MIDs does not become HIPAA compliant merely because each clinic has its own merchant profile.
The correct analysis begins with the vendor’s function and the data the vendor creates, receives, maintains, or transmits.
Ordinary financial processing is treated differently
HHS’s Business Associates guidance explains that a financial institution handling a consumer-conducted card payment, check, electronic funds transfer, or another activity that directly facilitates payment is providing its normal financial-transaction service rather than acting on behalf of the covered entity as a business associate merely because it moves the funds.
The current regulatory definition of “business associate” appears at 45 CFR 160.103. The eCFR version reviewed for this article was current through September 25, 2026.
The analysis changes when the vendor does more
A payment company may provide functions beyond ordinary card authorization and settlement. Examples can include:
- a patient-payment portal tied to account balances;
- PM/EHR integration;
- reconciliation services involving PHI;
- patient billing;
- data-hosting functions;
- token-vault services tied to patient profiles;
- text or email payment communications;
- call-center support; or
- analytics involving healthcare information.
If a vendor creates, receives, maintains, or transmits PHI on behalf of the covered entity while performing functions that bring it within the HIPAA business-associate definition, BAA obligations may arise. The answer depends on the service and data flow, not the company’s label as a “processor.”
When reviewing gateways, patient portals, reconciliation platforms, or other vendors that may handle PHI, a structured payment-vendor BAA review can help the practice document what data the vendor receives, what services it performs, and whether those activities require a business associate agreement.
What multiple locations change
For a multi-site organization, review:
- which covered entity or entities are contracting;
- which clinics and systems the vendor can access;
- user permissions;
- PM/EHR interfaces;
- PHI passed into reporting feeds;
- token-vault integrations;
- support access;
- subcontractors where applicable;
- data retention;
- termination requirements; and
- BAA coverage where required.
The number of MIDs is secondary to those data flows.
Keep unnecessary PHI out of processor metadata
Where the HIPAA minimum necessary standard applies, HHS says covered entities must make reasonable efforts to limit PHI uses, disclosures, and requests to the amount needed for the intended purpose; HHS also identifies exceptions, including disclosures to or requests by healthcare providers for treatment. The HHS minimum necessary guidance explains both the general rule and those exceptions.
That does not mean “never use any patient identifier” in a payment workflow. It means the organization should have a reasoned data design.
A payment integration normally does not need diagnosis names, detailed procedure descriptions, or unrelated clinical information simply to reconcile a deposit.
Does One MID or Many Change PCI DSS Scope?
Not by itself.
As of September 30, 2026, PCI SSC’s Document Library identifies PCI DSS v4.0.1 as the current published standard. PCI SSC retired v4.0 at the end of 2024, making v4.0.1 the supported active version.
Medical practices can verify the current version directly through the PCI Security Standards Council Document Library.
PCI SSC defines the cardholder data environment around the people, processes, technologies, and system components that store, process, or transmit cardholder data or sensitive authentication data, as well as certain connected components.
That is why “one MID has less PCI scope than five MIDs” is not a reliable rule.
What actually affects scope?
Examples include:
- how cards are accepted at each clinic;
- payment terminals;
- virtual terminals;
- call-center workflows;
- hosted payment pages;
- redirects or embedded payment components;
- workstations with access to payment systems;
- networks connected to payment devices;
- storage of cardholder data;
- third-party payment providers; and
- segmentation controls.
A MID per location medical practice configuration could create more administrative validation work in some environments, but MID count itself does not define the CDE.
PCI SSC also makes clear that outsourcing payment processing does not eliminate all merchant responsibility. Merchants remain responsible for understanding their compliance obligations and the compliance of relevant third-party providers.
Medical offices should map PCI responsibilities across their payment channels, including front-desk terminals, virtual terminals, patient payment pages, and other systems that may handle or affect payment-account data.
How PM/EHR Integration Should Map One MID or Many
The PM/EHR should provide the clinical and revenue-cycle context that the processor usually cannot.
A strong merchant account structure medical group implementation should preserve enough dimensions to answer both sides of reconciliation:
What happened to the patient’s balance?
and
What happened to the processor cash?
Useful fields include:
| Field | Primary Source | Purpose |
| Patient/account ID | PM | Match payment to patient ledger |
| Encounter | PM/EHR | Associate payment with applicable visit/accounting workflow |
| Location | PM/gateway | Site-level reporting |
| Department | PM/EHR | Internal allocation |
| Provider, where relevant | PM/EHR | Provider-level reporting |
| MID/merchant profile | Processor/gateway | Settlement attribution |
| Payment channel | Gateway/PM | Front desk, portal, phone, etc. |
| Processor transaction ID | Processor | Refund/dispute traceability |
| Authorization/reference ID | Processor | Transaction research |
| Batch ID | Processor | Settlement matching |
| Settlement date | Processor | Bank reconciliation |
| Gross amount | Processor | Collection matching |
| Refund amount | Processor/PM | Credit/refund matching |
| Processor fee | Processor, if available | Net-deposit accounting |
| Net deposit | Processor/bank | Bank reconciliation |
The processor transaction ID should not become the only identifier used for healthcare reporting.
A transaction ID tells accounting which processor event occurred. It does not replace the patient account, encounter, location, or provider dimensions maintained by the PM/EHR.
Different PM platforms may require a merchant configuration per organization, clinic, department, terminal, or channel. Others support different models. Verify the actual integration instead of assuming all systems map merchant profiles the same way.
When the PM/EHR and payment platform exchange structured transaction data, integrating payment records with EHR and practice-management workflows can reduce duplicate entry and make it easier to match patient-ledger postings with processor activity.
How to Reconcile Multi-Location Card Deposits Without Manual Spreadsheets
This should be one of the deciding tests for any merchant account structure medical group is considering.
If accounting still has to download five reports, manually color-code transactions, and rebuild the settlement in Excel every day, the architecture has not solved the underlying reconciliation problem.
Step 1 — Capture structured transaction dimensions at payment time
Every payment should carry the fields required to identify the correct clinic, department, account, and payment channel.
Use structured codes where possible instead of free-text descriptions.
Step 2 — Preserve the processor transaction ID
Store the transaction identifier returned by the processor or gateway in the PM/payment record.
This creates a link between patient-ledger posting and processor activity.
Step 3 — Import settlement information
Use the supported interface available from the processor, gateway, or PM vendor—such as an API, automated integration, SFTP feed, structured export, or other supported data connection.
Avoid designing a permanent process around rekeying totals.
Step 4 — Match individual transactions to batches
Connect charges and refunds to the batch or settlement grouping in which the processor included them.
The expected batch total should be reproducible from the transaction data.
Step 5 — Match processor settlement to the bank
Reconcile:
- gross charges;
- refunds;
- dispute adjustments;
- processor fees where deducted;
- reserves if applicable;
- other documented adjustments; and
- settlement timing.
Do not assume the bank deposit will always equal gross patient collections.
Step 6 — Produce location-level reconciliation
If one deposit covers several clinics, the reconciliation engine should still be able to show the amount attributable to each site.
This creates useful medical group deposit reporting without falsely presenting one bank deposit as several deposits.
Step 7 — Route exceptions automatically
Create review queues for:
- unmatched processor transactions;
- PM payments with no processor match;
- duplicate postings;
- missing refunds;
- amount mismatches;
- disputes;
- settlement-date differences;
- wrong-location postings; and
- unexplained bank variances.
Step 8 — Close the accounting period with an audit trail
The monthly close should preserve a traceable relationship from the PM payment to processor transaction, batch, settlement, and bank deposit.
That approach is more durable than manually reconstructing medical group deposit reporting after the fact.
Example 1: Three Clinics, One Legal Entity
Consider an illustrative medical group with three outpatient clinics.
All three operate under the same legal entity, use a common settlement account, share one central billing office, and use the same PM system.
The PM reliably records the clinic and provider associated with every patient payment. Refunds are managed centrally.
A consolidated merchant setup may work because reporting does not depend solely on the processor’s MID. The group can obtain clinic-level collections from its structured transaction data while maintaining centralized settlement.
The main weakness would appear if clinic metadata were missing or unreliable. Without it, accounting could receive one processor deposit but struggle to determine which site generated each component.
Example 2: Multi-Location Group Requiring Site-Specific Deposits
Now consider three clinics under a common organization where management requires each location’s patient payments to settle into a designated bank account.
A MID per location medical practice arrangement—or another processor-supported multi-settlement configuration—may make reconciliation cleaner.
Clinic A transactions flow through Clinic A’s merchant profile and can be matched directly to Clinic A’s bank deposit. The same applies to Clinics B and C.
The benefits are clearer site-level settlement and easier transaction ownership. The burdens are additional profiles, credentials, devices or configuration, reporting mappings, and cross-location refund controls.
Example 3: Newly Acquired Physician Practice
Assume a medical group acquires a physician practice with an existing processor relationship, stored payment credentials, recurring patient payment plans, unresolved refunds, and outstanding patient credits.
Immediately shutting down the legacy MID could create operational problems.
A controlled transition might preserve the legacy setup temporarily for appropriate pre-close refunds and existing payment workflows while the buyer verifies legal ownership, processor approval, token portability, recurring plan migration, PM conversion, bank settlement, BAA coverage, and dispute handling.
The longer-term merchant account structure medical group chooses should be implemented only after those dependencies are understood.
When to Restructure MIDs During a Medical-Practice Acquisition
An acquisition is a reason to review the merchant architecture—not automatically merge every MID on closing day.
An asset purchase and an equity/entity acquisition can leave different ownership structures. Without giving transaction-specific legal or tax advice, the payments team should determine who owns the post-close receivables, which legal entity will act as merchant, which TIN and bank account correspond to that operation, and what the acquirer requires before changing the merchant relationship.
| Acquisition Issue | Keep Legacy MID Temporarily? | New Merchant Setup? | Verify Before Cutover |
| Same legal entity survives | Possibly | Depends on processor requirements | Ownership updates, bank information, merchant agreement |
| New legal entity/TIN becomes merchant | May be useful during transition | Processor/acquirer should evaluate | Underwriting, agreement ownership, settlement account |
| Refunds for pre-close transactions | Often operationally useful | New MID may not provide access to old transactions | Original transaction access and refund responsibility |
| Recurring payment plans | May reduce disruption | Possibly | Token migration, schedule, consent and processor support |
| Stored payment tokens | Until migration is validated | Possibly | Portability and secure migration |
| PM/EHR conversion | Often phased | Depends | Mapping, duplicate-payment controls, transaction IDs |
| Post-close disputes | Legacy access may remain necessary | Not automatically solved by new MID | Contractual responsibility and transaction access |
A merchant account generally should not be treated as an asset that staff can simply point at a different unrelated legal entity without the processor or acquirer’s involvement.
Review:
- merchant agreement ownership;
- surviving legal entity;
- TIN changes;
- bank-account ownership;
- processor underwriting;
- existing tokens;
- payment plans;
- pre-close refunds;
- patient credits;
- chargebacks received after closing;
- statement descriptors;
- PM/EHR conversion;
- BAAs and vendor agreements; and
- accounting cutover.
If the acquired practice has active patient payment plans, inventory its recurring billing workflows before cutover so the migration accounts for payment schedules, stored credentials, cancellations, patient communications, and integration with the new billing environment.
Build a Medical-Group MID Architecture Inventory Before Changing Anything
Before choosing a new merchant account structure medical group leadership should build a complete inventory.
| Field | Document for Each Entity/Location |
| Legal entity name | |
| DBA | |
| TIN/EIN | |
| Organizational NPI, if applicable | |
| Relevant organizational subpart, if applicable | |
| Practice/enrolled location | |
| Clinic/location name | |
| Settlement account | |
| Current MID | |
| Processor/merchant profile | |
| Statement descriptor | |
| PM/EHR department | |
| Gateway profile | |
| Terminal/device IDs | |
| Payment portal configuration | |
| Refund owner | |
| Reconciliation owner | |
| BAA status where applicable |
The inventory creates a map between healthcare operations and payment infrastructure without pretending that the fields are equivalent.
A Practical Decision Tree for Choosing the MID Structure
Are different locations operated by different legal entities?
→ Have the processor/acquirer evaluate the merchant relationship appropriate to each entity. Do not infer the answer solely from NPI structure.
Same entity, but separate bank deposits are required?
→ Evaluate location-level MIDs or another supported settlement configuration.
Same entity and centralized settlement?
→ Determine whether the PM, gateway, and processor preserve enough location metadata for reliable reconciliation.
Do patients frequently move between locations?
→ Test patient-credit portability and cross-site refund access before isolating merchant environments.
Is provider-level reporting required?
→ First determine whether multi-provider payment reconciliation and provider attribution can be produced from the PM/EHR without physician-specific MIDs.
Are statement descriptors materially different by location?
→ Confirm what the processor/acquirer can actually configure and test the production result.
Is another practice being acquired?
→ Re-underwrite and remap legal ownership, banking, tokens, payment plans, refund access, and PM/EHR integrations before retiring legacy MIDs.
Common MID-Structure Mistakes in Medical Groups
| Mistake | Why It Creates Problems | Better Control |
| Assuming every NPI requires a MID | Confuses payer/provider identification with acquiring | Maintain separate healthcare-ID and payment-ID mappings |
| Treating TIN and MID as equivalent | Blurs tax identity and acquiring configuration | Document both separately |
| Consolidating deposits without location metadata | Makes clinic-level reconciliation difficult | Tag transactions at collection |
| Creating a MID for every physician only for reporting | Creates unnecessary fragmentation | Use PM/EHR provider attribution where appropriate |
| Allowing any clinic to manufacture a new refund/charge to move a credit | Breaks transaction and cash traceability | Reallocate internally when appropriate; refund through documented transaction workflow |
| Storing unnecessary clinical detail in payment metadata | Expands unnecessary exposure of healthcare information | Use appropriately limited identifiers |
| Assuming more MIDs automatically reduce PCI scope | Misstates PCI DSS scoping | Evaluate the actual cardholder data environment |
| Immediately closing acquired merchant profiles | Can disrupt old refunds, tokens, plans, or disputes | Plan a controlled cutover |
Medical Group Merchant Account Structure Checklist
Before approving the merchant account structure medical group will use, confirm:
- Every legal entity is identified.
- The TIN/EIN for each relevant entity is documented.
- Type 1 and Type 2 NPIs are mapped without treating them as merchant IDs.
- Organizational subparts and practice locations are documented where applicable.
- Each settlement bank account has a clear owner.
- Each MID and merchant profile is mapped to the appropriate entity and location.
- The PM/EHR records location independently of the MID.
- Provider-level reporting can be produced without unnecessary merchant fragmentation.
- Processor transaction IDs are stored for reconciliation.
- Statement descriptors have been tested.
- Cross-location payment allocation is documented.
- Patient-refund authority is documented.
- Acquired-practice legacy refunds and payment plans have a transition process.
- BAA requirements are evaluated based on vendor functions and PHI handling.
- PCI DSS scope is evaluated from actual card-data flows rather than MID count.
- Automated medical group deposit reporting can tie transactions to batches and bank deposits.
- Reconciliation owners and exception workflows are assigned.
Frequently Asked Questions
Does every doctor or NPI need a separate merchant account?
No. CMS’s NPI requirements identify healthcare providers for healthcare administrative transactions; they do not establish a general requirement that each NPI have a separate merchant account. Provider-level financial reporting can often be handled through the PM/EHR instead.
Can several medical-practice locations deposit card payments into one bank account?
Potentially, when the legal merchant relationship and processor/acquirer support that settlement structure. The organization should still preserve transaction-level location metadata so a consolidated deposit does not destroy site-level reporting.
Can different clinics have different statement descriptors?
Possibly, but descriptor configuration depends on the processor/acquirer and merchant setup. Do not assume a separate MID automatically produces a particular descriptor; verify and test the actual configuration.
How do we reconcile one processor deposit across several clinics?
Maintain the clinic/location with each transaction, preserve the processor transaction ID, match transactions to processor batches, match batches to bank settlement, and generate expected-versus-actual location reports. The bank may show one deposit while the reconciliation data preserves the underlying clinic allocations.
Which clinic should issue a patient’s refund?
Start with the original payment transaction. If the patient paid at one location but another location now services the account, distinguish patient-ledger reallocation from an actual processor refund. When a refund is required, follow the original transaction and the processor-supported workflow, using centralized billing where cross-site permissions require it.
Does using multiple MIDs change HIPAA compliance?
MID count alone does not determine HIPAA compliance. The relevant questions concern the covered entity, the vendor’s function, PHI data flows, access, safeguards, and whether the vendor qualifies as a business associate for the services being performed.
Does each MID automatically create a separate PCI DSS scope?
No. PCI DSS scope depends on the systems, people, processes, networks, and technologies involved in storing, processing, transmitting, or affecting the security of cardholder data. Separate merchant configurations may affect administration and validation, but MID count is not the controlling scope rule.
What should happen to existing MIDs when we acquire another practice?
Inventory them before changing them. Determine the surviving legal entity, settlement ownership, merchant agreement, processor underwriting requirements, stored tokens, recurring plans, refund access, patient credits, outstanding disputes, descriptors, PM conversion, and vendor/BAA arrangements.
Should provider-level reporting come from the processor or the PM/EHR?
The PM/EHR is often the more appropriate source for provider attribution because it knows the encounter, patient, rendering or billing provider, department, and financial class. Processor data remains essential for proving authorization, settlement, refunds, disputes, and bank reconciliation.
Choosing a Merchant Account Structure a Medical Group Can Actually Reconcile
The strongest merchant account structure medical group leaders can build is not necessarily the one with the fewest MIDs or the most MIDs. It is the structure that accurately follows legal ownership, patient-payment workflows, settlement banking, reporting requirements, integrations, refund authority, and operational responsibility.
CMS’s current NPI guidance confirms that individual providers, healthcare organizations, organizational structures, and practice locations have healthcare-identification purposes distinct from merchant acquiring. HHS guidance separately controls the HIPAA business-associate analysis, while PCI SSC’s current PCI DSS v4.0.1 framework governs payment-card security based on the actual cardholder data environment.
For some groups, one consolidated merchant environment with excellent transaction metadata will be the cleaner architecture. For others, separate location or entity merchant profiles will make medical group deposit reporting and reconciliation substantially easier.
Before adding or eliminating MIDs, map the legal entities, TINs, NPIs, practice locations, PM/EHR departments, merchant profiles, bank accounts, processor transaction IDs, refund permissions, payment channels, integrations, and vendor agreements.
That mapping turns the merchant account structure medical group uses from a collection of processor accounts into an auditable healthcare-payment architecture—one that preserves patient-payment traceability without creating unnecessary fragmentation.