By Robert Clifton September 30, 2026
When switching payment processors medical practice teams should inventory every active payment plan and stored credential, determine whether credentials can be securely migrated, review applicable BAA and PHI obligations, test the new PM/EHR integration, establish one recurring-billing cutover point, and reconcile the first billing cycle before declaring the migration complete.
Changing processors in healthcare is not simply a terminal swap. A medical practice may have stored payment credentials, recurring patient balances, authorizations, portal payments, refunds, pending reversals, practice-management integrations, patient identifiers, and—in some systems—protected health information moving through several vendors.
That makes switching payment processors medical practice operations partly a payments project, partly a systems migration, and partly a privacy and data-governance project. The practice needs to know exactly what moves, what stays behind, what must be disabled, and what must reconcile after the cutover.
Switching Payment Processors Medical Practice Teams: The Short Version
Before terminating an old gateway or processor, create a complete map of payment credentials, recurring plans, connected applications, patient-account identifiers, refunds, and data-handling relationships.
The following controls should be settled before production cutover:
| Migration Area | Confirm Before Cutover | Main Failure Risk |
| Stored credentials | Whether credentials can be securely migrated and how they will be mapped | Patients unexpectedly have to re-enter cards |
| Payment plans | Remaining balance, installment amount, next draft, retry status | Duplicate or missed payment |
| Card-on-file consent | Whether existing authorization still covers the arrangement | Authorization or billing dispute |
| BAA/PHI | Whether each vendor is actually a business associate and applicable termination duties | PHI remains accessible without appropriate controls |
| PM/EHR integration | Posting, mapping, refunds, failures and reconciliation | Correct payment reaches wrong patient ledger |
| Recurring billing | Exact old-system stop and new-system start | Double billing |
| Reporting | Final old-system records and first new-system settlement | Reconciliation gap |
| Access | Staff and former-vendor credentials after cutover | Unnecessary continuing access |
The central operational rule is simple: one system should be authorized to initiate each scheduled payment at any given time.
A medical practice should also avoid cancelling its old vault or gateway until it knows whether token migration stored patient cards can be performed securely. Once access is terminated, migration may become substantially harder or impossible depending on the vendor and contract.
Why Switching Payment Processors at a Medical Practice Is Different
A conventional merchant can often judge a migration by asking whether transactions authorize and settlements reach the bank.
Healthcare requires another level of reconciliation. A payment may successfully authorize and settle while still being assigned to the wrong patient, wrong guarantor, wrong balance, wrong location, or wrong payment plan in the practice-management system.
Medical payment environments can include:
- patient portals;
- EHR or PM integrations;
- virtual terminals;
- text-to-pay systems;
- recurring billing platforms;
- token vaults;
- patient statements;
- account and guarantor identifiers;
- automated posting services;
- refund and credit-balance workflows;
- settlement and reconciliation middleware.
This is why switching payment processors medical practice planning must include the patient-account ledger, not only the merchant bank account.
When payment processing is connected directly to the practice-management or EHR environment, integrated payment and EHR workflows can reduce separate data-entry steps, but the migration still needs to confirm that each transaction reaches the correct patient account, balance, and reconciliation record.
First Determine Which Vendors Actually Handle PHI
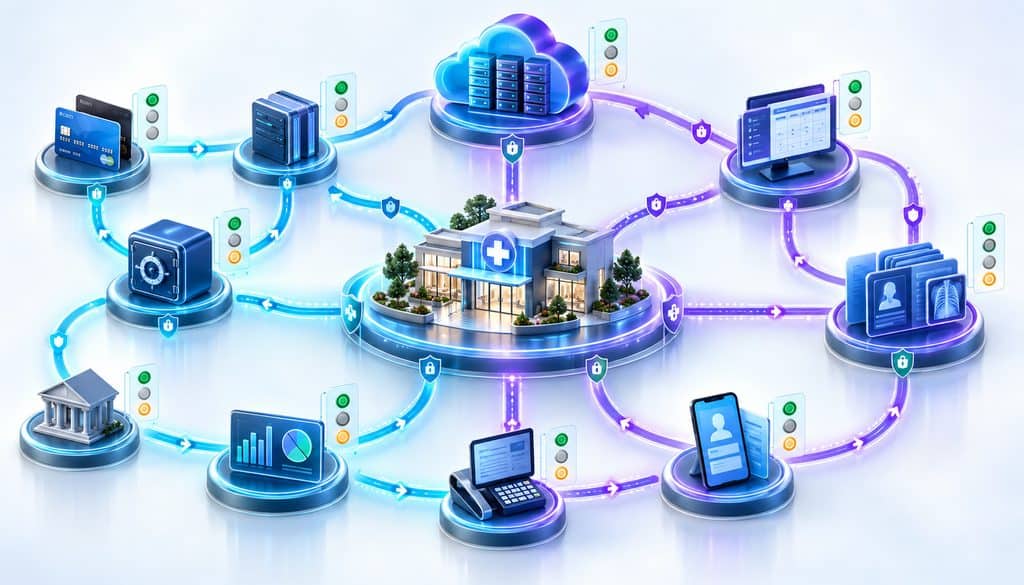
Do not begin the BAA analysis by assuming every company touching a card transaction is a HIPAA business associate.
Under HHS guidance, a business associate generally performs functions or services for a covered entity that involve creating, receiving, maintaining, or transmitting protected health information.
HHS also expressly distinguishes ordinary financial transactions: when a financial institution processes a consumer-conducted credit-card, debit-card, check, EFT, or similar funds-transfer transaction, it is providing its normal financial service rather than performing a function for the covered entity.
HIPAA classification turns on the service actually being performed. HHS specifically states that a financial institution conducting ordinary consumer-initiated card, check, EFT, or similar funds-transfer activity is providing its normal financial service rather than performing that activity on behalf of the covered entity; services involving PHI beyond that role may require a different business-associate analysis.
| Vendor Function | Information It May See | HIPAA Question |
| Basic card acquiring/processing | Payment-account and transaction information | Is it limited to ordinary financial processing? |
| Payment portal | Patient/account identifiers and balances | Does it create, receive, maintain, or transmit PHI for the practice? |
| PM/EHR payment integration | Patient ledger and payment information | What information moves and for what function? |
| Reconciliation service | Patient balances and transaction records | Is it performing a service involving PHI on the practice’s behalf? |
| Hosted payment-data storage | Data stored for the practice | Does the service maintain ePHI, even if staff rarely access it? |
HHS makes another important point for hosted technology: a cloud provider that maintains ePHI for a covered entity can qualify as a business associate even if it cannot read the encrypted information.
The practical result is that neither extreme is correct: not every processor automatically requires a BAA, and the word “processor” does not automatically exempt a vendor providing broader healthcare data services.
A practice evaluating when a payment vendor needs a BAA should look at what the vendor actually does with health information, not simply whether the company describes itself as a processor, gateway, portal, or software provider.
Inventory Every Patient Payment Plan Before Cutover
Before attempting to migrate recurring patient payment plans, establish an authoritative roster.
For each active, paused, delinquent, or otherwise open plan, capture:
- patient or account identifier;
- responsible party where applicable;
- current status;
- original plan balance;
- remaining balance;
- installment amount;
- payment frequency;
- next scheduled draft;
- expected final draft;
- stored-payment-method reference;
- existing token identifier;
- permitted expiration information;
- authorization or consent record location;
- failed-payment status;
- retry status;
- pending refund or reversal;
- unapplied credit;
- manually adjusted balances;
- system of record;
- migration exception status.
Do not assume “inactive” records can be ignored. A plan may be temporarily paused, waiting for an updated card, in retry status, or awaiting a refund while remaining operationally open.
Patient Payment-Plan Inventory Before Migration
Before switching payment processors medical practice administrators should be able to check each item below:
- Every open plan has a unique patient/account mapping.
- Remaining balances agree with the current patient ledger.
- The next scheduled payment is documented.
- Failed drafts and outstanding retries are identified.
- Pending refunds and reversals are separated from ordinary balances.
- Card-on-file or recurring authorization can be located.
- Each stored credential can be connected to the correct account.
- Expired or otherwise unusable credentials are flagged.
- One system has been designated as the plan system of record.
- Temporary migration exports have controlled access.
- CVV/CVC data is not included.
Do not place CVV, CVC, CID, CAV2, or equivalent card-verification values in the migration file. Under PCI DSS rules for card-verification-code storage, those values are sensitive authentication data and cannot be retained after authorization, including for card-on-file or recurring transactions.
Token Migration Stored Patient Cards: What Actually Moves?

A token is not simply another name for the full card number.
PCI SSC’s tokenization guidance describes a token as a surrogate value used in place of the primary account number, or PAN. But tokenization architecture varies, and the token-to-PAN relationship depends on the particular implementation.
That distinction matters because gateway tokens are frequently specific to the vault or provider that created them. Network tokens are a different technology layer. A practice therefore should not assume that a token generated by Vendor A can simply be pasted into Vendor B’s platform.
For token migration stored patient cards, four models are commonly encountered operationally:
| Migration Model | Patient Action | Practice Exposure to PAN | Main Dependency |
| Vault-to-vault credential migration | Usually none | Minimal/no direct exposure | Cooperation and technical compatibility |
| Provider-to-provider PAN transfer | Usually none | Practice should remain outside raw transfer | Controlled PCI-compliant process |
| Credential migration followed by new token creation | Usually none | Normally limited | Incoming provider’s vault process |
| Patient re-entry | Required | Low | Outreach and patient completion |
Not every provider supports every model.
A practice should not request that thousands of raw card numbers simply be emailed or delivered in an ordinary spreadsheet. The better question is whether the outgoing custodian can perform a controlled provider-to-provider migration into the incoming environment.
How to Request a Token or PAN Migration
When switching payment processors medical practice teams should send a structured migration request to both the outgoing and incoming providers.
Ask:
- Who operates or controls the existing vault?
- What kind of token is currently stored?
- Are those tokens usable outside the existing environment?
- Can a direct vault-to-vault transfer be performed?
- If tokens are not portable, is an approved provider-to-provider credential transfer available?
- What merchant authorization is required before release?
- Which data elements will be transferred?
- How are expired credentials handled?
- Will cardholder name or billing postal code transfer where needed?
- How are stored-credential or recurring-transaction attributes recreated?
- How will the migrated credential map back to the correct patient/account ID?
- Is a test file or test migration available?
- How are rejected or unmapped credentials reported?
- What rollback procedure exists?
- When will the outgoing vault stop accepting new drafts?
- What information remains with the outgoing provider?
- When will practice access to the old platform end?
- What data-disposition documentation is available under the contract?
How long does token migration take?
There is no universal industry migration period that applies to every processor or gateway.
Timing depends on the outgoing provider’s cooperation, contractual terms, token count, vault architecture, security review, field mapping, receiving system, test migration, production transfer, and exception handling.
For that reason, a medical practice processor transition checklist should begin well before the planned termination date. A published vendor timeline can be used for planning only when it applies to that specific migration; it should not be presented as an industry rule.
What Happens to the BAA When the Old Vendor Relationship Ends?
For BAA termination payment vendor planning, first confirm that the vendor is actually acting as a business associate for the service in question.
Current 45 CFR §164.504(e) requires an applicable business-associate contract to address PHI at termination. If feasible, the business associate must return or destroy PHI that it still maintains and retain no copies. If return or destruction is infeasible, contractual protections must continue and further use or disclosure must be limited to the purposes that make return or destruction infeasible.
For a vendor that is acting as a business associate, the contract must address what happens to PHI when the relationship ends. Under 45 CFR §164.504(e)’s business-associate contract requirements, PHI must be returned or destroyed at termination when feasible; when that is infeasible, the protections of the agreement must continue and further use or disclosure must be limited to the reason retention remains necessary.
The practice should inventory:
| Question | What to Verify |
| What PHI exists? | Production databases, reports, support records, exports and applicable backups |
| Must it be returned or destroyed? | BAA language and applicable HIPAA requirements |
| Is return/destruction infeasible? | Vendor explanation and continuing restrictions |
| What do subcontractors hold? | Downstream BAA obligations |
| When does portal access end? | Contract and technical shutdown procedure |
| What evidence exists? | Closure confirmation or destruction documentation if required/agreed |
HHS’s model BAA likewise addresses return or destruction after termination and continued protections where disposition is infeasible.
Does HIPAA require a certificate of destruction?
Do not turn this into a universal HIPAA requirement.
The regulatory rule requires the BAA to address return or destruction as described above. It does not, by itself, establish a universal requirement that every terminated business associate produce a separately titled “certificate of destruction.”
A particular BAA may require one. A practice may also negotiate written confirmation as an operational control.
That distinction makes a BAA termination payment vendor checklist much more accurate: distinguish the HIPAA requirement, the signed contract, and additional evidence the practice wants for its records.
Do Existing Card-on-File Authorizations Survive the Change?
A new processor does not automatically mean every patient must sign a new card-on-file authorization.
Instead, review whether the existing agreement still supports:
- the same medical practice or payee;
- the same underlying patient obligation;
- the same payment plan;
- the same amount or permitted variable amount;
- the same frequency;
- the continuing storage and use of the credential;
- recurring or installment payments where applicable.
The current Visa public rules are dated April 18, 2026, and Visa continues to maintain rules governing stored credentials and recurring transaction processing. Mastercard’s public rules currently available are dated June 2, 2026.
Card-network requirements are implemented through acquirers, processors, and technical message specifications, so a medical practice should confirm how the incoming provider will preserve or establish the correct stored-credential and recurring-payment treatment.
Fresh authorization is more appropriate when the old authorization is missing or unclear, the responsible legal entity changes, the payment-plan terms materially change, or applicable law, network rules, or the merchant agreement require new documentation.
The processor change alone should not be presented as a universal legal trigger for re-papering every patient.
How to Migrate Recurring Patient Payment Plans Without Double Billing
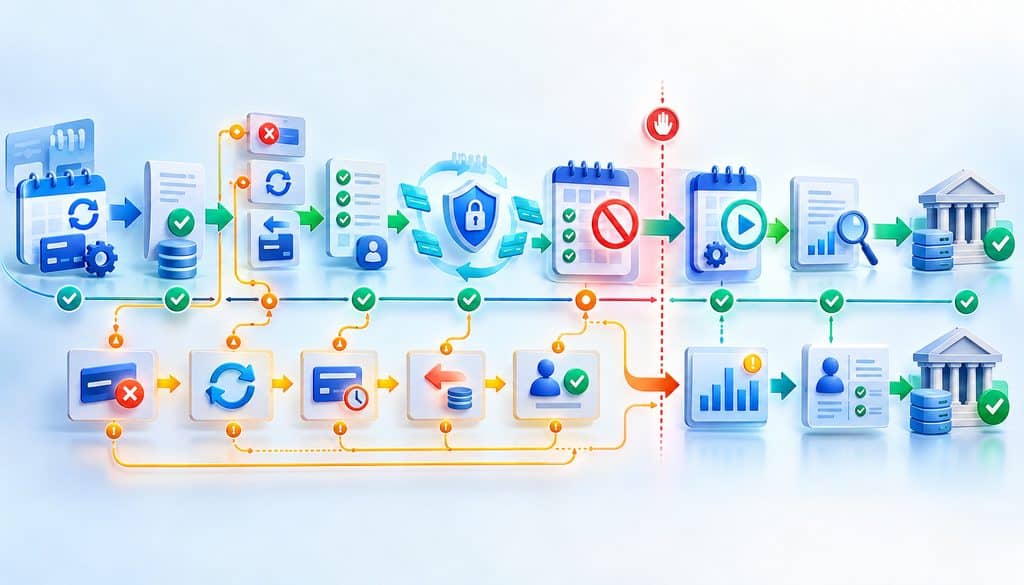
When practices migrate recurring patient payment plans, the safest control is that only one billing engine can initiate a particular scheduled draft.
Use this cutover sequence:
- Choose the production migration date.
- Create the authoritative payment-plan roster.
- Define the final old-system processing period.
- Stop creating new plans in the old platform at the agreed freeze point.
- Process and post transactions through the freeze period.
- Resolve or document failed drafts and retries.
- Record pending refunds, reversals, and chargebacks separately.
- Transfer eligible credentials.
- Import future plan schedules and remaining balances.
- Validate account-to-token mapping.
- Reconcile balances against the patient ledger.
- Disable future drafts in the old system.
- Verify that the disablement actually took effect.
- Activate validated plans in the new system.
- Review exceptions daily during the initial cutover period.
- Reconcile the first complete recurring cycle.
Never leave both recurring engines active “just in case.”
If a patient pays off a balance during the migration window, update the authoritative roster before new schedules are activated. If an old transaction settles after the initial export, post it and recalculate the balance rather than carrying the stale pre-settlement amount into the new system.
Practices using recurring billing for clinic and specialist patient balances should identify the remaining balance, next draft date, retry status, and stored-payment reference for every open plan before moving future schedules to the new platform.
Preventing Duplicate and Missing Drafts
For switching payment processors medical practice operations, batch settlement totals are not sufficient.
| Control | Main Problem It Prevents |
| Authoritative payment-plan roster | Missing patient plans |
| Exact old-system stop point | Duplicate drafts |
| Exact new-system activation point | Premature drafts |
| Patient/account/token mapping | Payment assigned to wrong account |
| Remaining-balance reconciliation | Overcollection |
| Retry ownership | Two systems retrying the same failed payment |
| Refund and reversal register | Incorrect patient balance |
| First-cycle exception report | Silent migration failure |
Suppose the new processor deposits exactly the expected total. That does not prove the migration was correct if one patient’s $150 payment was posted to another patient’s account.
A successful healthcare processor conversion therefore requires both merchant-level settlement reconciliation and patient-account-level reconciliation.
What to Verify in the New Provider’s BAA
This section applies where the new provider’s actual functions make it a business associate.
A BAA termination payment vendor review should not be limited to the outgoing contract. Before signing with the incoming business associate, verify that the agreement appropriately addresses:
- permitted and required uses of PHI;
- safeguards;
- reporting of inappropriate uses or disclosures;
- security-incident and breach obligations as applicable;
- subcontractors;
- support for applicable access, amendment, and accounting requirements;
- PHI return or destruction at termination;
- circumstances involving infeasible destruction;
- continuing restrictions on retained PHI;
- termination rights.
These subjects track the business-associate requirements in 45 CFR §164.504(e).
Other useful contract provisions may go further than HIPAA itself. Data-export formats, migration support, backup treatment, post-termination account access, subcontracted support, service levels, or written disposition confirmation can be negotiated operational safeguards rather than universal statutory requirements.
Verify the PM/EHR Integration Before Signing
A processor should not pass acceptance testing merely because a card transaction succeeds.
Before switching payment processors medical practice teams should identify whether the integration is native, API-based, middleware-based, batch/file-based, or manually reconciled.
Pre-Signing Integration Test Checklist
Test:
- patient/account matching;
- stored-credential mapping;
- point-of-service payments;
- copay posting;
- partial payments;
- recurring-plan posting;
- failed recurring drafts;
- retries;
- voids;
- refunds;
- chargebacks;
- payment links;
- portal payments;
- text-to-pay;
- batch totals;
- settlement reconciliation;
- user permissions;
- role-based access;
- audit logging;
- duplicate-message handling;
- interface interruptions;
- downtime procedures.
A test payment should be traced end to end: from authorization through the processor, into the correct patient account, through any interface or middleware, and finally into settlement and reconciliation. A successful approval at the terminal or payment page does not establish that the downstream PM/EHR posting worked correctly.
PHI in Migration Exports: Move Only What Is Needed
Payment exports may contain more than card-related information.
Depending on configuration, they may include patient names, internal account identifiers, invoice numbers, email addresses, telephone numbers, payment histories, plan descriptions, notes, or practice location information.
Do not automatically classify every field as PHI without examining its context. But where PHI is involved and the HIPAA minimum-necessary standard applies, covered entities generally must take reasonable steps to limit uses, disclosures, and requests to the minimum necessary to accomplish the intended purpose. HHS also identifies exceptions to that standard, including certain treatment disclosures and uses or disclosures authorized by the individual.
The practice can rely on the HHS minimum-necessary guidance rather than a generic vendor interpretation.
For migration files:
- Determine which identifiers are actually needed.
- Remove unnecessary fields before transfer where practical.
- Use an approved secure transfer mechanism.
- Restrict access to migration personnel.
- Avoid ordinary email for raw payment-account data.
- Maintain a controlled copy only as long as legitimate operational and applicable retention needs require.
- Remove temporary migration files and permissions after reconciliation under the practice’s applicable policies.
A CSV export should not become an uncontrolled secondary patient-payment database simply because it was created for a one-time conversion.
Medical Practice Processor Transition Checklist
The following medical practice processor transition checklist is a planning model, not an industry-mandated timeline. A simple migration may require less preparation; a complex multi-location EHR migration may require considerably more.
Approximately 6–8 Weeks Before the Target Cutover
- Review termination and notice provisions.
- Map processor, gateway, vault and integration vendors.
- Determine which vendors handle PHI.
- Review applicable BAAs.
- Request token or credential migration.
- Inventory active payment plans.
- Locate patient authorizations.
- Confirm PM/EHR compatibility.
- Identify refunds, disputes and retries in progress.
Approximately 4–6 Weeks Before Cutover
- Agree on the credential-transfer mechanism.
- Map old identifiers to new identifiers.
- Configure the incoming merchant and gateway environment.
- Establish user roles.
- Begin PM/EHR testing.
- Review patient-facing payment forms.
- Define the recurring-billing freeze and cutover procedure.
Approximately 2–4 Weeks Before Cutover
- Conduct a test migration if supported.
- Compare source and destination record counts.
- Validate selected token-to-account mappings.
- Test payment, void and refund transactions.
- Test recurring-plan behavior.
- Test failed-payment handling.
- Test patient-ledger posting.
- Train billing and front-office staff.
- Document escalation paths for failed migration records.
Final Week
- Freeze unnecessary configuration changes.
- Produce the final authoritative plan roster.
- Reconcile balances.
- Identify the final old-system draft.
- Process the final credential transfer.
- Validate migrated records.
- Disable future old-system billing at the defined point.
- Confirm that the new scheduler remains disabled until approval.
Cutover Day
- Process controlled live transactions.
- Confirm patient-account posting.
- Verify authorization and settlement behavior.
- Test a void or refund workflow where operationally appropriate.
- Activate only verified recurring plans.
- Review exception queues.
- Confirm that the old scheduler cannot originate future drafts.
First Week After Cutover
- Reconcile migrated accounts.
- Review failed transactions.
- Correct mapping exceptions.
- Match settlements to patient ledgers.
- Resolve duplicate or missing records immediately.
- Track pending refunds and reversals separately.
- Confirm staff are no longer using the old payment workflow.
First Complete Recurring Cycle
- Compare the expected plan roster with actual drafts.
- Investigate skipped plans.
- Investigate unexpected transactions.
- Reconcile remaining balances.
- Confirm old recurring credentials are no longer initiating charges.
- Close migration exceptions.
Approximately 30 Days After Cutover
This is an operational review point, not a statutory deadline.
Confirm that unnecessary outgoing-vendor access has ended, applicable PHI disposition requirements have been addressed, temporary migration files and permissions are removed where appropriate, and unresolved exceptions have an assigned owner.
This medical practice processor transition checklist should be adapted to the actual contract, EHR, gateway, vault and practice structure.
Realistic Migration Example
Assume a specialty practice has 540 stored credentials, 76 active patient payment plans, portal payments, a PM integration, and monthly recurring drafts.
When switching payment processors medical practice administrators first export the plan inventory. They discover four expired payment methods, three failed drafts awaiting action, two pending refunds, and one plan that a patient paid off by phone but that had not yet been closed in the old recurring system.
The outgoing gateway confirms that most eligible credentials can be transferred directly to the incoming PCI-compliant environment. The practice does not receive a spreadsheet of raw PANs.
A limited test migration is completed first. Staff verify that migrated credentials map to the intended patient accounts and that test transactions post correctly in the PM system.
Before production transfer, the practice posts all old-system activity and recalculates every remaining plan balance. The old scheduler is then disabled for future payments.
The incoming scheduler is not activated until staff confirm the credential mapping and plan balances. The four patients with unusable credentials enter the normal payment-method update workflow instead of being manually reconstructed from incomplete data.
During the first new recurring cycle, the billing team compares the expected roster with actual results. One mapping exception is corrected and the two previously pending refunds remain tracked separately until completed.
The example does not depend on an assumed universal migration period. The operational sequence—inventory, migrate, reconcile, disable, activate, reconcile again—is what matters.
Common Processor-Migration Mistakes
The most common failures are preventable.
Cancelling the old gateway before migration
Once access or the contractual relationship ends, the practice may lose the cooperation or functionality required for credential export.
Assuming every token is portable
A token can be tied to a particular vault or technical environment. Verify portability instead of assuming it.
Requesting raw PANs by ordinary email
Credential migration should use an approved secure provider-to-provider process where available, not an improvised spreadsheet workflow.
Migrating tokens without patient/account mapping
A usable credential is of little value if the practice cannot reliably determine which patient or responsible party it belongs to.
Ignoring inactive-looking plans
Paused or failed plans may still have a remaining obligation or future retry.
Leaving both recurring schedulers active
This creates an obvious duplicate-draft risk.
Migrating balances too early
Post final old-system payments, reversals and adjustments before declaring the destination balance authoritative.
Forgetting pending refunds
A refund initiated in the outgoing system can remain operationally relevant after new payments have begun.
Testing settlement but not PM/EHR posting
The bank deposit and the patient ledger solve different reconciliation questions.
Assuming one BAA covers every integrated vendor
Each relationship should be evaluated based on the functions performed and PHI handled.
Deleting source data before validating migration
Keep the records needed for migration verification subject to applicable retention and security policies.
Leaving former-user access open indefinitely
Close unnecessary user, administrative and vendor access after the appropriate verification and wind-down work is complete.
Frequently Asked Questions
Can stored patient cards be transferred to a new processor?
Potentially. Token migration stored patient cards depends on the outgoing vault, receiving system, credential type, provider cooperation, contract, and technical migration capability. Some credentials can be migrated without patient action; others may require the patient to provide a payment method again.
How long does a token migration take?
There is no authoritative universal number of days. The timeline depends on security approval, source-vault cooperation, field mapping, test files, production transfer, record volume and exception handling.
Can a medical practice download full patient card numbers?
Do not assume it can or should. Ask whether the outgoing provider can perform an approved direct transfer to the incoming compliant environment so that practice personnel do not unnecessarily handle raw PANs.
Do patients need a new card-on-file authorization after the processor changes?
Not automatically. Review whether the existing authorization still covers the same practice, underlying obligation, amount structure, frequency and stored-credential arrangement. Obtain updated authorization when the existing record is inadequate or applicable legal, contractual or network requirements call for it.
Does the outgoing vendor have to destroy patient data?
If the vendor is a business associate for the relevant service, 45 CFR §164.504(e) requires the BAA to address return or destruction of PHI at termination when feasible. If it is infeasible, contractual protections continue and further uses and disclosures must be appropriately limited.
Does HIPAA require the vendor to issue a destruction certificate?
HIPAA’s BAA provisions do not establish a universal standalone certificate requirement. The BAA may require written certification, or the practice may negotiate it as evidence that contractual disposition steps were completed.
Can the old and new processors run patient payment plans simultaneously?
The same scheduled obligation should not have two systems independently authorized to draft it. To migrate recurring patient payment plans safely, define the final old-system run and the new-system activation point.
What if a patient payment occurs during the migration?
Post the transaction to the authoritative patient ledger, adjust the remaining balance, and establish which system owns any retry or follow-up action before activating the future schedule.
Does every medical payment processor need a BAA?
No. HHS expressly distinguishes ordinary consumer-conducted financial transactions from functions or services performed for a covered entity that involve PHI. Evaluate what the vendor actually does.
What should be tested in the EHR or practice-management system?
Test patient mapping, payment posting, stored-credential association, recurring plans, partial payments, voids, refunds, failed drafts, portal payments, settlement reconciliation, permissions, audit logs, duplicate messages and downtime handling.
Switching Payment Processors Medical Practice Success Means More Than the First Approved Transaction
The goal of switching payment processors medical practice operations is not merely to obtain the first successful authorization. That proves only that one transaction can reach the payment system.
The project is complete when stored credentials are accounted for, token migration stored patient cards exceptions are resolved, active plans reconcile, the old scheduler is disabled, the new scheduler is verified, patient ledgers post correctly, applicable BAA termination payment vendor obligations are addressed, and the first recurring billing cycle closes without unexplained duplicates or omissions.
For a practice preparing to migrate recurring patient payment plans, the best safeguard is disciplined sequencing: inventory first, verify credential portability, reconcile old activity, migrate securely, disable the old scheduler, activate the new scheduler, and reconcile again.
That is the core of a dependable medical practice processor transition checklist—and the difference between merely replacing a processor and completing a controlled healthcare payment migration.